Frequently Asked Questions (FAQs)
1. What is considered a thin endometrium?
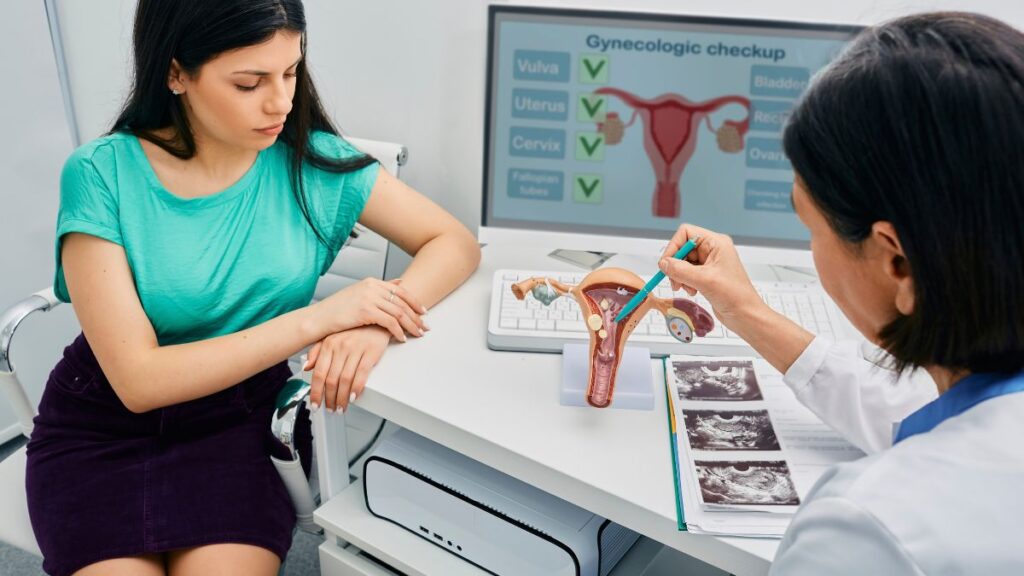
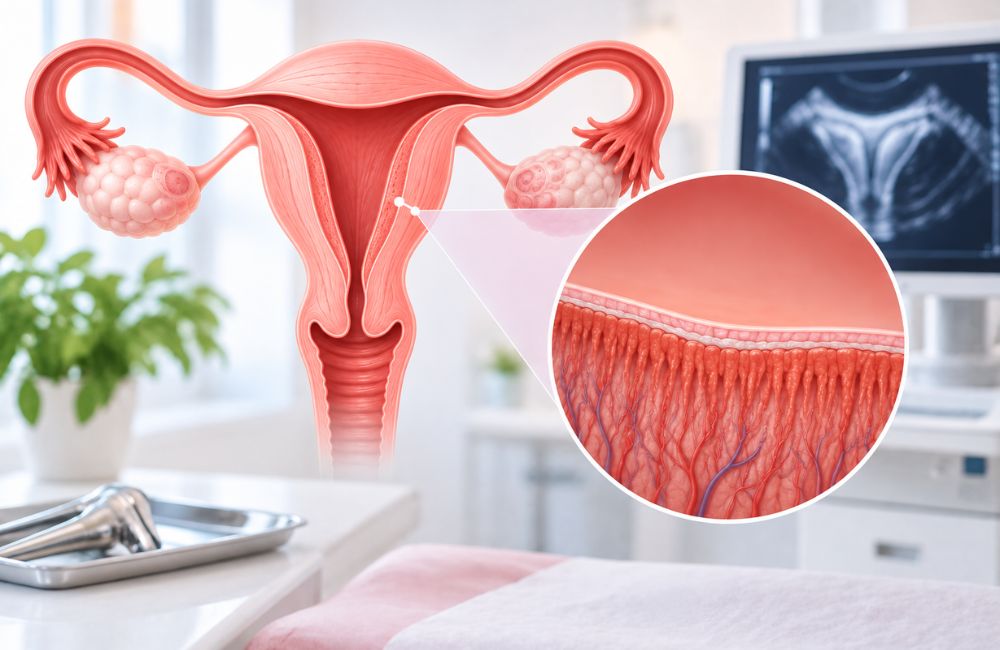
In assisted reproductive treatments, an endometrial thickness measuring less than 7 mm on transvaginal ultrasound around the time of ovulation or progesterone administration is commonly defined as a thin endometrium.
2. What is the ideal endometrium thickness for pregnancy?
An endometrial thickness between 8 mm and 12 mm with a distinct trilaminar (triple-line) appearance is generally considered ideal for embryo implantation. However, pregnancies can and do occur with measurements outside this range, as tissue quality and receptivity also play vital roles.
3. Can IVF be successful with a thin uterine lining?
Yes. While clinical data indicate that optimal lining depth improves overall implantation odds, a thin lining does not make pregnancy impossible. Many individuals achieve viable pregnancies after protocol adjustments or individualized embryo transfer timing.
4. What are the main thin endometrium treatment options?
Treatment depends on the root cause and may include adjusting estrogen dosages and delivery methods, switching cycle protocols (such as using natural or stimulated frozen embryo transfers), and performing a hysteroscopy to evaluate and treat uterine adhesions.
5. Does PRP help in treating a thin endometrium?
Intrauterine PRP is being explored for its potential to stimulate cellular growth in stubborn, thin linings. However, medical bodies such as ESHRE and ASRM emphasize that scientific evidence remains limited, and it is not currently recommended as a standard or proven clinical routine.